
Loading your page…
Loading your page…
Published by Korean Association of Cardiopulmonary Resuscitation · Class of Recommendation and Level of Evidence / GRADE
This clinical guideline presents the 2025 Korean Guidelines for Cardiopulmonary Resuscitation: Part 9, focusing on Neonatal Resuscitation. It covers evidence-based recommendations adapted from ILCOR consensus science to fit the Korean healthcare context. Detailed protocols include umbilical cord management (deferred clamping or milking), initial thermal and airway management steps, respiratory support (CPAP, PPV, and avoidance of routine sustained inflations), endotracheal intubation incorporating video laryngoscopy, chest compressions, epinephrine and volume expansion dosing, post-resuscitation glucose and therapeutic hypothermia management, and ethical guidelines on withholding or discontinuing resuscitation.
Key Takeaways
Key updates from the 2020 guidelines include: (1) extending the applicable period of neonatal resuscitation throughout the first 28 days of life and NICU hospitalization until discharge; (2) introducing specific DCC and I-UCM cord management pathways based on vigor and gestational age; (3) introducing video laryngoscopy as a preferred intubation tool; (4) withdrawing the routine recommendation against initiating resuscitation with 100% oxygen in term/late preterm infants; (5) recommending against the routine use of sustained inflations lasting >=5 seconds; (6) formally advising against the use of sodium bicarbonate; and (7) extending the time threshold to consider the discontinuation of resuscitation from 10-20 minutes to approximately 20 minutes after birth.
For newborn infants who are vigorous immediately after birth and do not require additional resuscitation, deferred umbilical cord clamping for at least 60 sec is suggested.
For term infants and late preterm infants who are not vigorous immediately after birth, intact umbilical cord milking is suggested.
For preterm infants born at <37 weeks' gestation who do not require immediate resuscitation at birth, deferred umbilical cord clamping for at least 60 sec is recommended.
In preterm infants born between 28 0/7 and 36 6/7 weeks' gestation in whom DCC is not performed, intact umbilical cord milking (I-UCM) may be a reasonable alternative to early cord clamping (ECC) to improve hematologic outcomes.
For preterm infants born at <28 weeks' gestation, intact umbilical cord milking (I-UCM) is not recommended.
To maintain body temperature in preterm infants born at <34 weeks' gestation, the use of a plastic bag or wrap and a hat is strongly recommended.
Routine suctioning of the mouth and nose at birth in newborn infants born through clear amniotic fluid is not recommended.
For nonvigorous newborn infants born through meconium-stained amniotic fluid, routine laryngoscopy with tracheal suctioning at the initiation of resuscitation is not recommended. Instead, resuscitation should be initiated with immediate PPV to rapidly establish effective ventilation.
When ECG equipment is available, the use of a three-lead ECG is suggested for newborn infants requiring resuscitation.
For preterm infants with spontaneous breathing at birth who require respiratory support, the use of CPAP as initial respiratory support is preferable to endotracheal intubation and PPV.
For preterm infants receiving PPV at birth due to bradycardia or ineffective breathing, the routine use of sustained inflations lasting >=5 seconds is not recommended.
When resources and educational conditions permit, the use of video laryngoscopy is recommended over direct laryngoscopy for endotracheal intubation, particularly when intubation is performed by less experienced providers.
The use of sodium bicarbonate is not recommended, both during brief cardiopulmonary resuscitation (CPR) and in prolonged resuscitation scenarios, even when adequate ventilation has been established and there is no response to other therapies.
For newborn infants born at >=36 weeks' gestation with moderate to severe hypoxic-ischemic encephalopathy (HIE), therapeutic hypothermia should be initiated according to clearly defined protocols and provided in centers capable of multidisciplinary care and long-term follow-up.
In newborn infants who require CPR after birth, if the return of spontaneous circulation is not achieved despite the completion of all appropriate resuscitative steps and the exclusion of reversible causes, it is appropriate to consider discussions regarding discontinuation of resuscitation with the team and the family at approximately 20 minutes after birth.
Clinical Topic
Neonatal resuscitation
Objectives
To provide updated, evidence-based medical recommendations for neonatal resuscitation immediately after birth and during the neonatal period, standardizing clinical practice in Korea to improve neonatal survival and long-term neurodevelopmental outcomes.
Target Patient Population
Newborn infants immediately after birth, during the transitional period, and throughout the neonatal period (up to 28 days after birth) when gas exchange failure causes cardiovascular compromise (extending until discharge for NICU-hospitalized infants).
Diagnostic Criteria
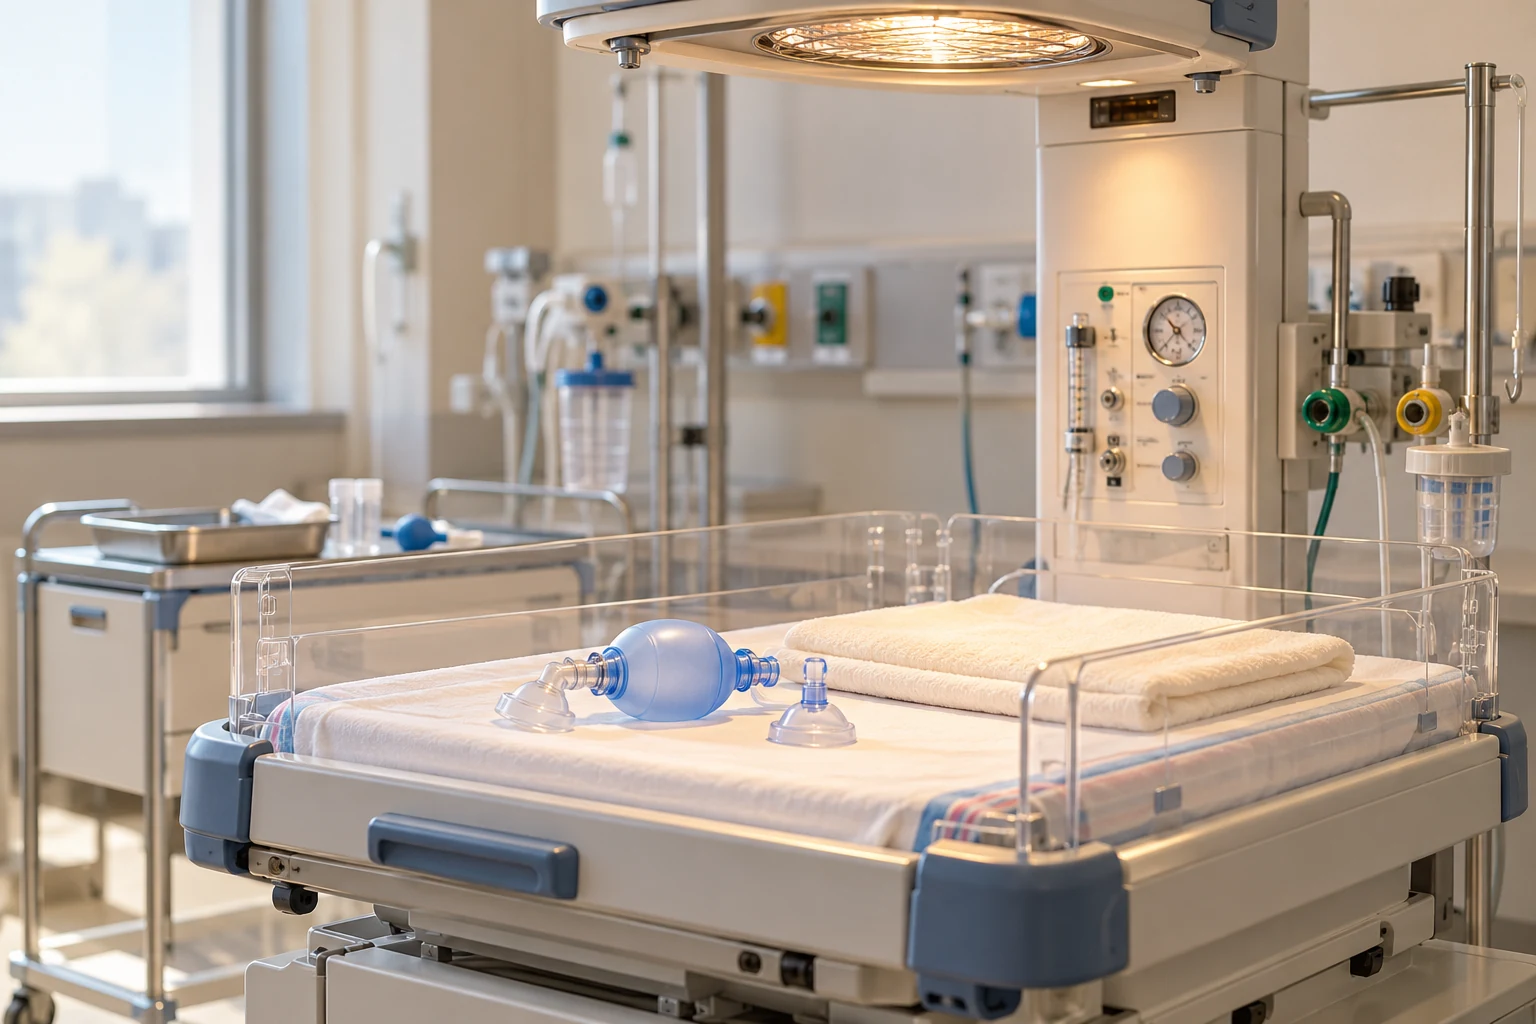
At birth, three rapid assessment questions are utilized to determine the need for resuscitation: (1) Is the infant preterm? (2) Does the infant have poor muscle tone? (3) Is the infant not breathing or not crying effectively? If the answer to any of these questions is 'yes,' the infant is transferred to a radiant warmer to initiate resuscitation steps.
Target Providers
Therapeutic Area
NeonatologyGuideline Scope
Inclusion Criteria
Exclusion Criteria
Care Settings
Special Populations
System: Class of Recommendation and Level of Evidence / GRADE
Evidence Distribution
Evidence Levels
Recommendation Strength
Contraindications
Monitoring Guidance
Rapid and accurate heart rate assessment is critical; a three-lead ECG is suggested as the fastest and most accurate method for infants requiring resuscitation. Preductal oxygen saturation (SpO2) must be continuously monitored via pulse oximetry. For infants with unintended hypothermia, temperature and blood glucose must be monitored frequently to prevent hyperthermia and hypoglycemia. Serial blood glucose monitoring is also required post-resuscitation.
Difficulty
advanced
Estimated Read Time
60 minutes
Learning Paths